GLP-1 weight loss drugs impact both healthcare economics and the food industry
Bottom line (updated 2026-10-01): The clearest change is higher drug spending and changes in some patients’ hunger and eating. Some patients may need less care later, but we are not sure if this lowers total health costs. We also lack proof that these drugs have changed the food world as a whole.
What's this about?
People disagree about whether GLP-1 (a type of drug) will change health care and the food world.
These drugs help some people lose weight, eat less, and lower some health risks.
What supporters say
- GLP-1 drugs can lower hunger, so some people may eat less, buy less food, or pick new foods.
- These drugs create large, ongoing costs for people, health plans, and drug budgets.
- The drugs may stop some heart and weight-related illness, which could lower later care costs.
What critics say
- We do not yet know if GLP-1 drugs have changed the whole food world.
- Money saved by avoiding illness may cover some of the drugs’ high costs.
How to read this
The number of points on each side does not show which side is right; strong proof matters more.
The bottom line
The clearest change is higher drug spending and changes in some patients’ hunger and eating.
Some patients may need less care later, but we are not sure if this lowers total health costs.
We also lack proof that these drugs have changed the food world as a whole.
GLP-1 weight-loss medicines are already changing healthcare spending and may be changing what people eat. But the evidence is much stronger for effects on drug budgets and individual patients than for claims about the food industry or total healthcare costs.
The case for
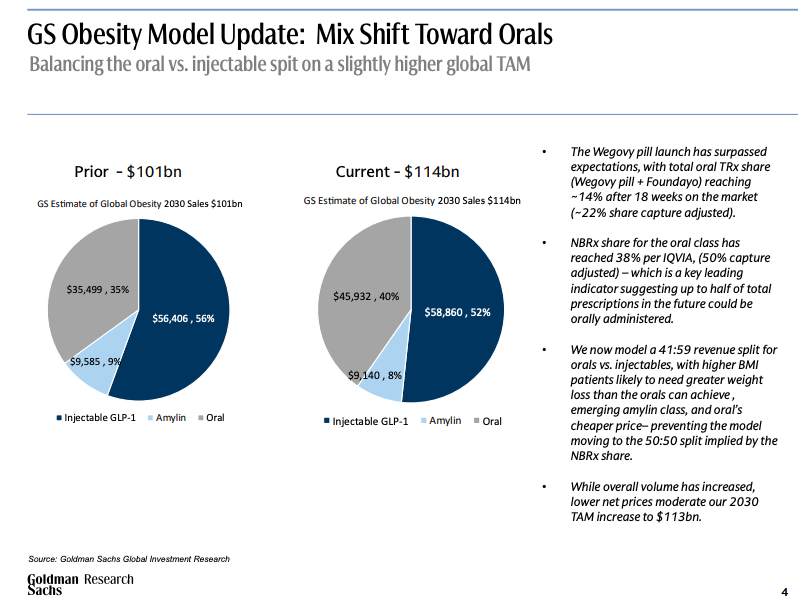
The clearest effect is direct: GLP-1 medicines create substantial, recurring healthcare spending. National data from Croatia show that use of these drugs and spending on them have risen. Economic analyses suggest the final budget impact depends on the drug’s price, whether insurers reimburse it, how long patients remain on treatment and which costs are included. The Croatian figures do not show what will happen in every health system, but they establish a healthcare-economic effect in the basic sense of increased pharmaceutical spending. 1
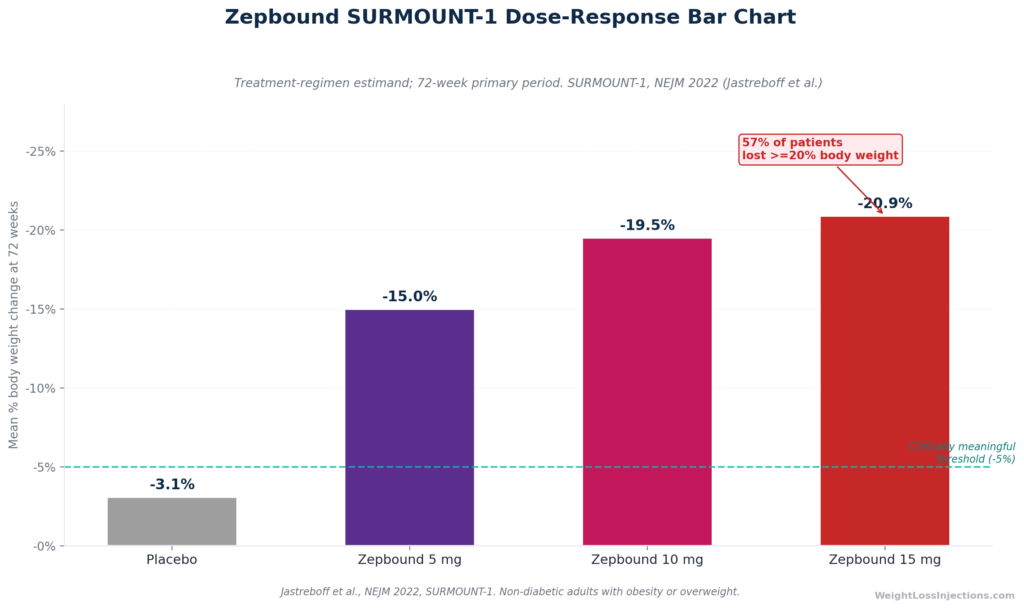
The drugs could also change healthcare costs later by preventing illness. Trials have found substantial weight loss with tirzepatide, while semaglutide reduced major cardiovascular events in a selected group of adults with overweight or obesity and established cardiovascular disease (see Figure 3). These results support the possibility of savings from fewer complications and less medical care. They do not, however, prove that total spending falls after the cost of the medicines and long-term treatment is included. 2
There is strong evidence that GLP-1 treatment changes individual appetite and eating behavior. Reviews and observational studies report reduced appetite and changes in nutrition-related habits. The drugs’ effects on appetite and stomach emptying provide a medical explanation for why people may eat less, buy smaller portions or choose different foods. This creates a credible link between treatment and food purchasing, even though the size of that effect has not been measured across the whole economy. 3
The case against
The available evidence does not show that GLP-1 medicines have already changed the food industry as a whole. Studies document changes among users, but they do not provide comprehensive sales data showing a measurable shift in total demand for groceries, restaurants or packaged foods. Lower overall consumption could also be offset by changes in the kinds of food people buy, rather than by a simple decline across every category. 4
Nor can rising drug spending alone determine whether the medicines increase or reduce overall healthcare costs. In one randomized trial, people who continued semaglutide maintained or extended their weight loss, while those switched to a placebo regained weight. This suggests that some patients may need ongoing treatment to preserve the benefit. Real-world treatment persistence is variable, and gastrointestinal side effects can lead to extra costs, treatment interruptions or discontinuation.
The financial balance also depends on access, price, dose, insurance coverage and the health of the people being treated. Avoided heart disease and other complications may offset part of the drug bill, but the cited evidence does not provide a cross-country budget analysis that combines medicine costs, side effects, treatment duration and prevented illness. 5
The bottom line
GLP-1 medicines clearly affect healthcare economics, chiefly through recurring drug spending, and there is strong evidence that they can alter food choices and eating behavior among individual users. The evidence supports those conclusions with considerable confidence.
The broader claims are less settled. It remains unproven that the drugs have produced an industry-wide change in food sales, and the evidence does not yet show whether they reduce total healthcare spending once ongoing treatment, weight regain, side effects and avoided disease are counted. Overall, the claim is supported in a qualified way: the direct effects are well established, while the net healthcare impact and economy-wide food-market consequences remain uncertain.
Pros — Supporting Arguments
Cons — Opposing Arguments
Figures & data

All contributions are reviewed for clarity, balance, and evidence. The strongest insights are elevated into the argument graph — with credit to you.
Help improve this analysis →